
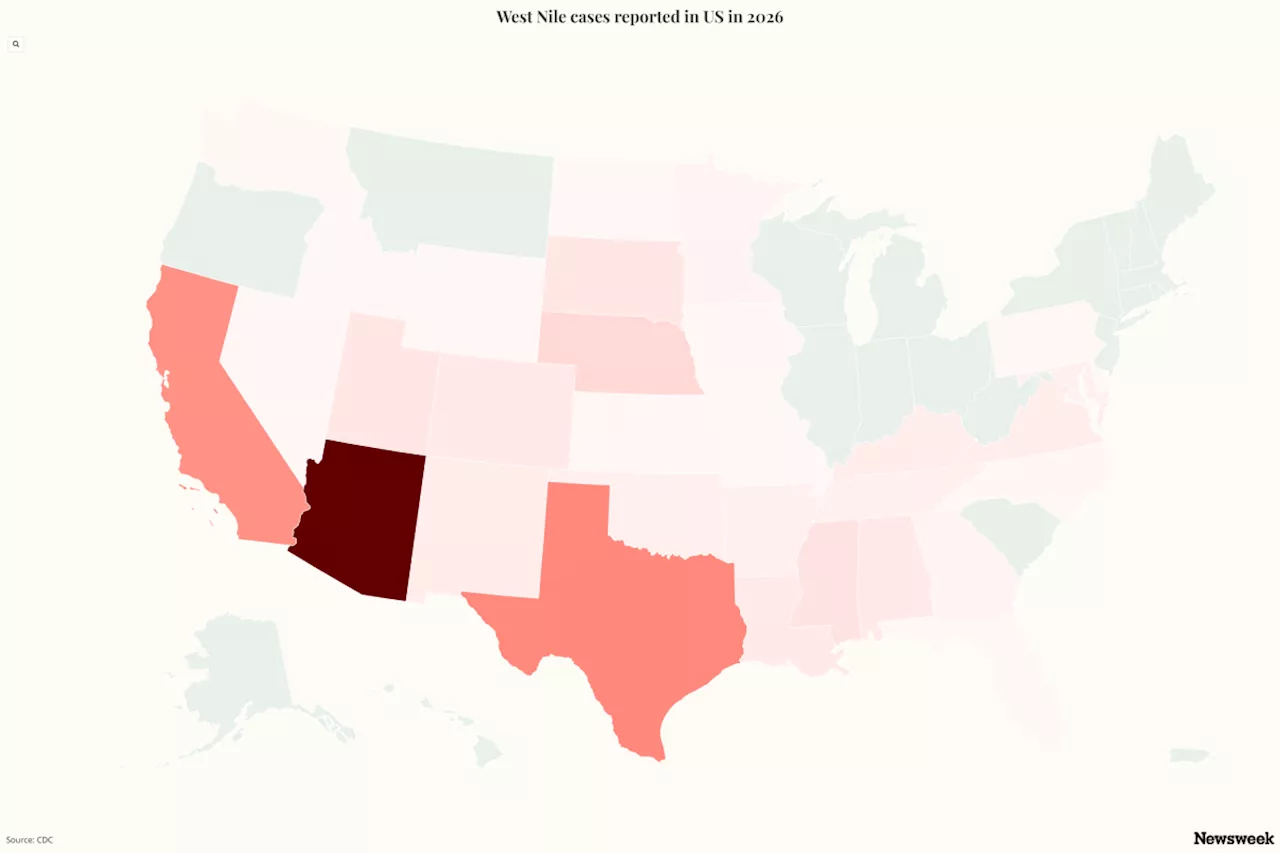
The U.S. Centers for Disease Control and Prevention (CDC) has identified 222 human West Nile virus infections across 32 states. This surge includes 156 severe neuroinvasive cases and eight fatalities as of mid-August.
Arizona's 76 cases lead a growing national surge
Current data from the CDC's ArboNET surveillance system indicates that the West Nile virus is concentrating heavily in the Southwest.. Arizona has reported the highest volume of infections with 76 cases, followed by Texas with 31 and California with 29. These figures highlight a significant regional clustering, though the virus remains a nationwide threat during the peak summer and early autumn mnoths.
Beyond human infections, the CDC reports widespread non-human activity, with the virus detected in various bird populations and mosquitoes. This animal-to-insect transmission cycle suggests that the virus is circulating in many regions where human cases have not yet been clinically confirmed. Because mosquitoes act as the primary vector, the presence of the virus in local wildlife serves as an early warning system for potential human outbreaks.
The 10 percent mortality rate for neuroinvasive disease
While the majority of West Nile virus infections are mild or invisible, the subset of neuroinvasive cases presents a grave risk. According to the CDC, approximately 10 precent of people who develop severe neurologic disease—which affects the brain and spinal cord—ultimately die. This season has already seen eight deaths, with five occurring in Arizona and three in California.
The risk is not distributed equally across the U.S. population. The CDC notes that adults aged 65 and older, as well as individuals with weakened immune systems or chronic medical conditions, are significantly more likely to suffer from neuroinvasive complications. For these high-risk groups, symptoms can escalate from a high fever to tremors, paralysis, or vision loss, often requiring intensive hospitalization.
In contrast, the vast majority of the population experiences a much lighter course of illness. The CDC estimates that roughly 80 percent of infected individuals remain entirely asymptomatic, while about 20 percent develop "West Nile fever," characterized by joint pain, headache, and vomiting.
A persistent threat since the 1999 New York outbreak
The current spike is part of a long-term ecological shift in North America. Since the West Nile virus was first detected in New York in 1999, it has successfully established itself in every state within the contiguous United States. The virus's ability to persist depends on a specific biological triad: susceptible bird populations, compatible mosquito species, and a climate that supports insect breeding.
Public health officials emphasize that preventing the bite is the only reliable defense. The CDC recommends using EPA-registered insect repellents and wearing long-sleeved clothing.. Furthermore, the removal of standing water in flower pots, bird baths, and clogged gutters is critical to disrupting the breeding cycle of the mosquitoes that carry the virus from birds to humans.
The gap in jurisdictional surveillance and underreported mild cases
A critical uncertainty remains regarding the true scale of this year's outbreak. As the CDC reports, human infections are frequently underreported, particularly the mild cases that do not require hospitalization. This suggests that the 222 confirmed cases are likely a fraction of the actual number of people infected across the 32 affected states.
Furthermore, the lack of reported cases in 18 states—including Alaska and Hawaii—may be a reflection of varying surveillance intensities rather than a total absence of the virus. Because mosquito and animal monitoring varies by jurisdiction, some regions may simply be less equipped to detect the virus's presence before it reaches a human host. This inconsistency in data collection makes it difficult to determine exactly where the "front lines" of the current spread are located.
Comments 0