
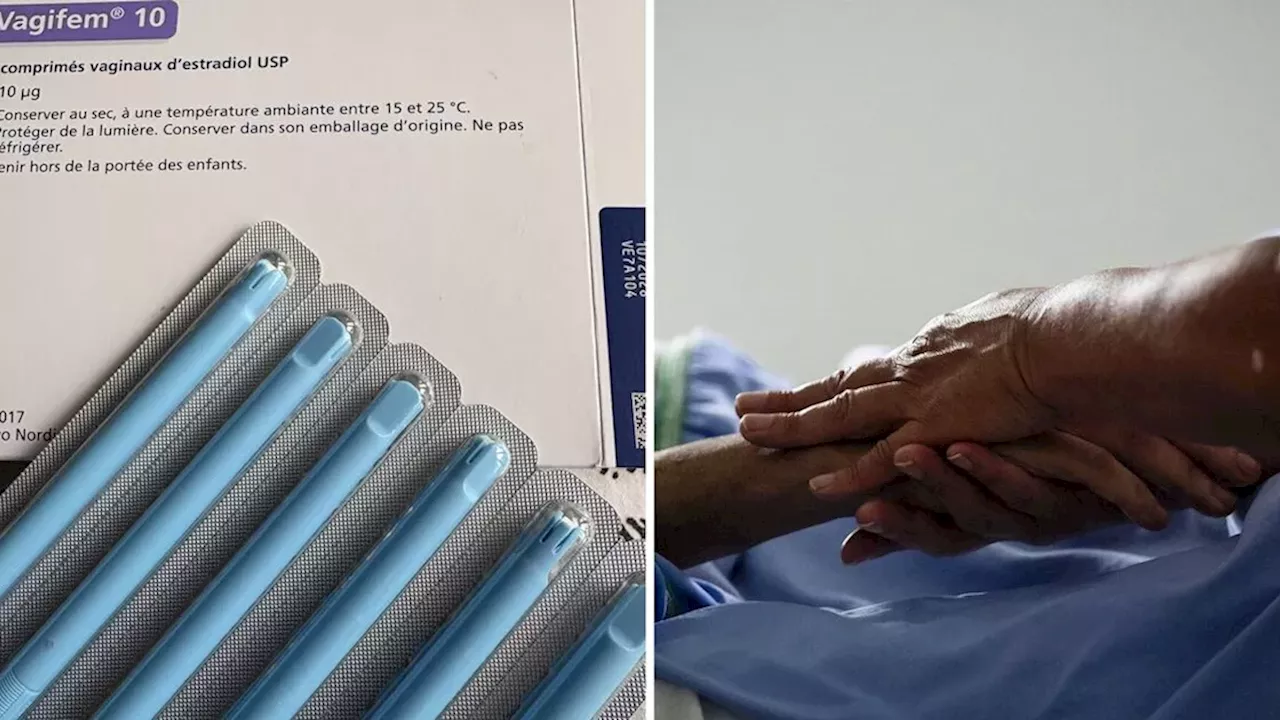
Research involving nearly 1.9 million women suggests that vaginal estrogen significantly reduces the risk of sepsis, hospitalization, and death for those with recurrent urinary tract infections (UTIs). The findings, published in the journal Urology, highlight a massive gap between clinical potential and actual patient treatment.
The 1 .9 million-woman study in Urology
A large-scale study led by Justin LaClair at the Albany Medical Center has provided robust evidence that low-dose vaginal estrogen—administered via cream or pill—offers protection against the most severe complications of recurrent UTIs. By tracking nearly 1.9 million women who experienced at least two infections, researchers were able to compare outcomes between those prescribed the hormone treatment and those who were not. the results showed that across all age groups, the estrogen group experienced significantly lower rates of life-threatening sepsis and death.
The strength of these findings was unexpected by some of the researchers involved. Dr. Elise De, a urologist and professor at Albany Medical College in New York, told the report that the data was surprisingly powerful.. The study underscores a biological reality: as estrogen levels drop during and after menopause, vaginal and urinary tissues become thinner and more fragile, allowing harmful bacteria to multiply more easily.
A dismal 5.1% uptake rate in the U.S.
Despite the clear clinical benefits, the repot highlights a staggering lack of implementation in standard care. In the United States, LaClair noted that only about 5.1% of women received vaginal estrogen within two months of being diagnosed with a recurrent UTI. This figure is part of a broader global trend where only 5% to 25% of women with chronic infections are offered the therapy.
The human cost of this treatment gap is high. The report shares the story of 92-year-old Olga, who died from sepsis caused by an undetected UTI after her family sought help for what they thought was a stroke.. In Canada, where up to 60% of adult women experience at least one UTI in their lifetime, the strain on the healthcare system is significant, with UTIs accounting for roughly 500,000 physician office visits annually.
The 1980s hormone myth vs . 2025 FDA reality
Much of the hesitation to prescribe estrogen stems from historical misinformation regarding systemic Hormone Replacement Therapy (HRT). in the 1980s, HRT delivered throughout the body was linked to increased risks of breast cancer, creating a lasting stigma that continues to influence modern prescribing habits. However, medical experts emphasize that vaginal estrogen is fundamentally different because it is localized to the urinary and vaginal areas.
The regulatory landscape has shifted to reflect this distinction. In 2025, the FDA removed "black box" warnings on low-dose vaginal estrogen, and similar regulatory updates are being discussed in Canada. Furthermore, both U.S. and Canadian Urological societies updated their guidelines in 2025 to recommend the treatment for peri- and postmenopausal women struggling with recurrent infections.
How to educate non-urologists like Dr. Fox Robichaud?
A major hurdle remains the dissemination of this knowledge to the broader medical community. Dr. Alison Fox Robichaud, a critical care physician at McMaster University and president of the Canadian Sepsis Foundation, noted that while she prescribes the treatment in hospital settings, she often receives "funny looks" from nursing staff and patients. This suggests a significant knowledge gap among healthcare providers who are not specialists in urology.
This lack of awareness raises several critical questions for the medical establishment:
- How can specialized urological guidelines be effectively integrated into the training of general practitioners and nursing staff?
- Why does the 82% of Canadian women who do not recognize the link between menopause and UTIs remain unreached by preventative education?
- Will the viral reach of social media,such as Dr. Rachel Rubin’s Instagram post which garnered 3.7 million views,become a primary driver for medical literacy where formal institutions have failed?
Comments 0