
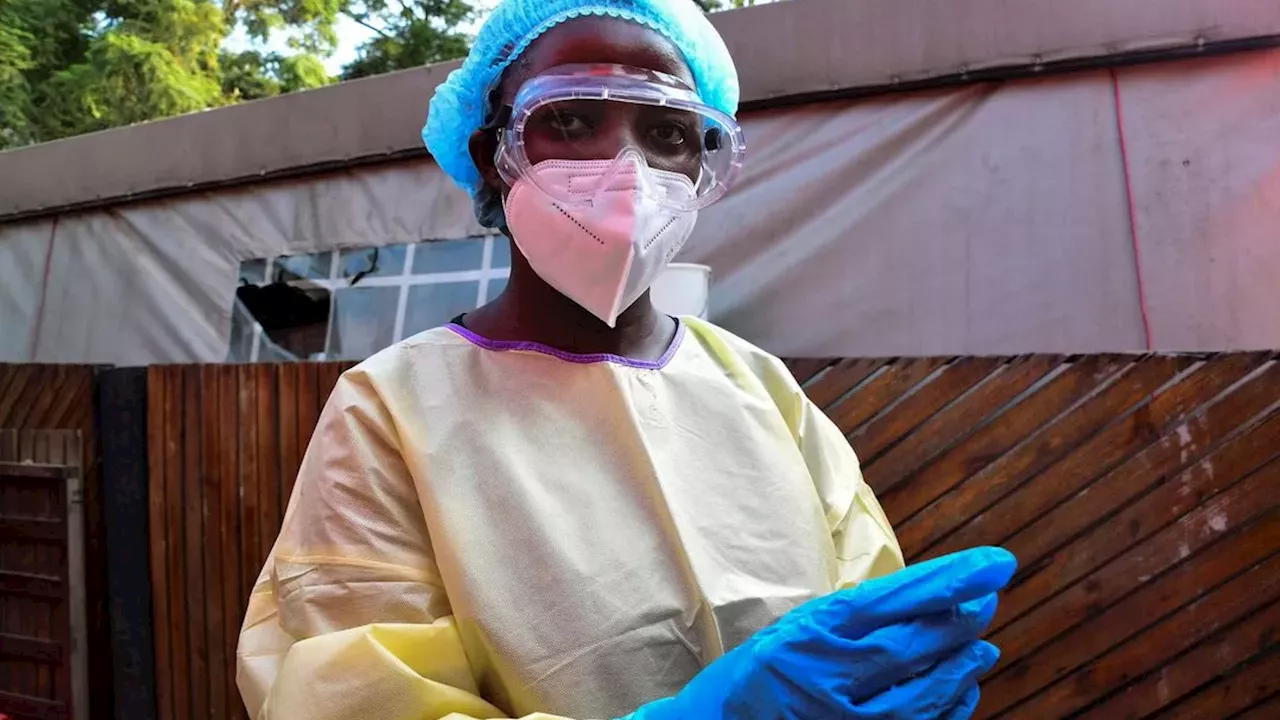
A rare Bundibugyo strain of Ebola has spread across the Democratic Republic of the Congo, Uganda, Kenya, and Nigeria. The Africa Centres for Disease Control and Prevention has labeled the situation an "extremely serious threat" due to its unprecedented geographic reach.
From the DRC to Abuja: The most geographically widespread Ebola outbreak in history
The current Ebola outbreak is distinguished by its rapid movement across African borders, marking the first time the virus has reached such a wide distribution. According to the Africa CDC, the virus originated in the Democratic Republic of the Congo last year before appearing in Uganda, Kenya, and most recently, Nigeria. In Nigeria, authorities identified a woman who had traveled from Uganda to Abuja as the first confirmed case; she is currently isolated and receiving treatment.
In Kenya, the outbreak has been concentrated within a single cluster of nine confirmed infections. one patient, a 24-year-old, remains in isolation after testing positive while in quarantine. This individual is a relative of the first confirmed Kenyan patient, who died in Nairobi on October 5. While eight of the nine Kenyan patients have reported positive treatment outcomes, the movement of the virus across these diverse regions suggests a high risk of further transmission.
The 50% mortality rate and the crisis in eastern DRC
The human cost of the Bundibugyo strain has been most severe in the eastern provinces of the Democratic Republic of the Congo. As reported in the source, the outbreak has infected nearly 9,400 people and resulted in at least 4,500 deaths, leading to a crude mortality rate of approximately 50% within the DRC. This health crisiis is exacerbated by existing regional instability, including civil conflict, food insecurity, and widespread malnutrition.
The psychological toll on these communities is profound, adding a layer of trauma to populations already displaced by war. Dr. Mirella Riccardi, a mental-health specialist with Médecins Sans Frontières, highlighted the social isolation faced by the sick, citing a Congolese teacher whose neighbors avoided all contact until humanitarian teams could disinfect homes and transport the ill. this intersection of disease and social collapse complicates containment efforts and increases the vulnerability of the population.
The October trial of Ervebo and the Moderna-Oxford race
Because there is currently no approved vaccine specifically for the Bundibugyo strain, health officials are attempting to repurpose existing technology.. Jean Kaseya, the Director General of the Africa CDC, announced that a full-scale human trial of Ervebo—a vaccine already approved for the Zaire strain of Ebola—will begin by the end of October in the Democratic Republic of the Congo. The trial aims to determine if Ervebo provides cross-protection against the Bundibugyo strain.
Beyond the Ervebo trials, other pharmaceutical efforts are in the early stages of clinical development. The source notes that research teams from the University of Oxford and the US-based company Moderna are developing their own vaccine candidates. However, the World Health Organization has warned that the pace of the outbreak is currently outstripping surveillance and containment efforts, making the success of these trials a critical priority for global health security.
The 44 close contacts in Nigeria and the risk of community spread
A primary concern for health officials is whether the virus has moved beyond isolated clusters into the general population. In Nigeria, the health ministry is currently monitoring and quarantining 44 close contacts of the woman who arrived in Abuja. While the Kenyan health ministry maintains there is no evidence of community transmission outside its single cluster, the broader alert from the World Health Organization suggests that the global response must be strengthened to prevent a wider catastrophe.
Several critical questions remain unanswered regarding the transmission chain. It is not yet clear how the virus moved from the DRC to Uganda and then to Nigeria and Kenya, nor is it verified if the 44 contacts in Nigeria have remained asymptomatic. Furthermore, the report focuses heavily on the Africa CDC and WHO perspectives, leaving it unclear if local governments in the affected regions have the financial resources to sustain long-term quarantine and surveillance without massive international aid.
Comments 0